Ask most people how their health insurance works and they’ll say “family floater” — often without knowing what that word is actually doing to their cover the day someone in the family gets seriously ill. The choice between individual vs family floater vs super top-up health insurance isn’t a technicality for the fine print; it decides whether your policy is still standing after the claim that matters most, or whether it’s already been used up by someone else’s hospital bill. Here’s what each structure actually does, and how to combine them properly.
Every health insurance policy eventually gets tested the same way: not on the day you buy it, but on the day someone in your family is actually admitted to a hospital. That’s when the structural choice you barely thought about while comparing premiums online — individual, floater, or top-up — either does its job quietly, or turns into the worst kind of surprise. Most people default to whatever a bank relationship manager or a comparison site nudges them toward, without understanding that these three structures aren’t just pricing tiers of the same thing. They behave completely differently the moment a real claim happens, and getting the choice wrong is invisible right up until it isn’t.
Individual vs Family Floater vs Super Top-Up
These three aren’t different price points on the same product — they’re three different ways of structuring who’s covered, for how much, and what happens once a claim starts eating into that number.
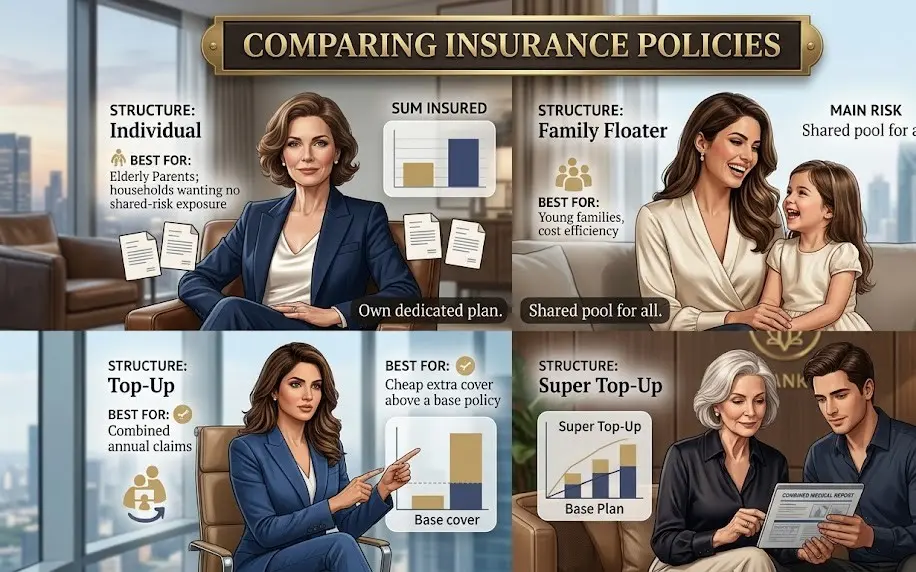
Each family member gets their own, separate sum insured. If your spouse claims ₹8 lakh for a surgery, your own ₹10 lakh cover and your children’s cover remain completely untouched. It costs more in total than an equivalent floater because you’re effectively buying full-size cover for every single person, but it removes any risk of one member’s illness eating into another’s protection.
One shared sum insured “floats” across everyone named on the policy — typically self, spouse, and children. It’s usually cheaper than buying the same total cover as separate individual policies, which is exactly why it’s the default most families are sold. The trade-off: if one member has a large claim early in the policy year, whatever’s left of the sum insured is all that’s available for everyone else for the rest of that year.
Both sit on top of a base policy (your own, or an employer’s group cover) and activate only once a “deductible” threshold is crossed in a policy year — at a much lower premium than buying that much additional base cover outright. The distinction between the two matters more than most buyers realise: a plain top-up plan pays out only if a single hospitalisation crosses the deductible on its own. A super top-up pays out once the combined total of all claims in the policy year crosses that same deductible — so three smaller hospitalisations that add up past the threshold are covered, where a plain top-up would pay nothing for any of them individually. For that reason, a super top-up is almost always the better version of the two for a similar premium.

Which Structure Actually Fits Your Household
There’s no single right answer here — it depends on who’s in your household and how old they are. But a few patterns hold up consistently well.
- A family floater is usually the most cost-effective starting point
- Add a super top-up once income allows, to raise total protection cheaply
- Children’s claims tend to be smaller and less frequent, so a shared floater rarely gets strained
- A super top-up above the floater covers the rare large claim affordably
- Buy separate individual (often senior-citizen-specific) policies for parents rather than adding them to the family floater
- Older members have both a higher chance of claiming and higher premiums, so folding them in inflates the whole floater’s cost and claim risk for everyone else
IRDAI removed the long-standing maximum entry age of 65 for new health insurance policies effective April 1, 2024 — insurers are now required to offer products across all age groups, including senior citizens, and can no longer refuse a policy outright to someone with a serious pre-existing condition like cancer, heart disease, or kidney failure, though pricing and specific terms still vary by insurer and case. This makes buying a standalone policy for ageing parents, rather than leaving them uninsured or folded into a floater, a genuinely realistic option today, even later in life.
Worked Example: A Family of Four, Two Ways
Take a household of four — two adults in their late thirties, two children — comparing a family floater against buying four separate individual policies for a similar total cover.
The floater is cheaper, but for meaningfully less total protection per person. The approach most planners land on isn’t “pick one” — it’s a hybrid: keep the floater as the base for the whole family, and layer a super top-up of, say, ₹20–25 lakh on top with a deductible roughly matching the floater’s sum insured. That combination usually costs far less than scaling the floater itself to a bigger number, while still protecting against the one large claim that could otherwise exhaust everyone’s cover in a single hospitalisation.
What Health Insurance Covers — And What It Doesn’t
- In-patient hospitalisation expenses (room rent, ICU, surgery, doctor’s fees, medicines while admitted)
- Pre-hospitalisation expenses for a defined period (commonly 30–60 days) before admission, and post-hospitalisation expenses for 60–90 days after discharge
- Day-care procedures that don’t require a 24-hour hospital stay (cataract surgery, chemotherapy sessions, and similar)
- Ambulance charges up to a specified limit
- AYUSH treatment (Ayurveda, Yoga, Unani, Siddha, Homeopathy) in many current-generation policies
- Routine outpatient (OPD) consultations and diagnostics, unless a specific OPD add-on or rider is purchased
- Cosmetic or purely elective procedures not medically necessitated by illness or accident
- Self-inflicted injury, and treatment linked to substance misuse
- Dental and vision care beyond what’s accident-related, unless separately added
- Any condition or treatment specifically named as excluded in your policy wording — always worth reading before a claim, not after
Waiting Periods, Co-Pay & the Fine Print
- Initial waiting period: Typically 30 days from policy start, during which only accident-related claims are payable — standard illness claims aren’t covered until this period passes.
- Pre-existing disease (PED) waiting period: Following an IRDAI directive effective April 2024, insurers can no longer impose a pre-existing disease waiting period longer than 36 months (3 years) — reduced from the earlier 48-month cap. Many insurers offer shorter periods; always check the specific policy’s figure rather than assuming the maximum applies.
- Specific-disease/procedure waiting period: Certain conditions and procedures (commonly named ones include cataract, hernia, and joint replacement) often carry their own separate waiting period, typically shorter than the PED one, before they’re covered.
- Co-payment: A clause requiring you to bear a fixed percentage of every claim yourself — common in senior-citizen plans and some budget products. A 20% co-pay on a ₹5 lakh claim means you personally pay ₹1 lakh regardless of your sum insured; it’s worth checking for explicitly before buying, especially for parents’ policies.
- Restoration benefit: Reinstates your sum insured (fully or partially) once it’s exhausted within a policy year, so a second unrelated hospitalisation later in the year isn’t left with no cover. Not every policy includes this by default — check whether it’s automatic or a paid add-on.
- Room rent limits: Many premium, no-sub-limit plans exist today as a straightforward product design choice, but plenty of standard and budget policies — including IRDAI’s own standardised entry-level product — still cap room rent at a fixed amount or percentage of sum insured, alongside a mandatory co-pay. A capped room rent can trigger a proportionate cut to the entire claim, not just the room charge, which is why this specific clause is worth checking before buying rather than assuming it no longer applies. Separately, IRDAI’s October 2020 guidelines standardised how insurers define and calculate these proportionate deductions across the industry — they clarified the rules, but didn’t remove sub-limits themselves.
Quick Comparison Table
| Structure | Sum Insured | Best For | Main Risk |
|---|---|---|---|
| Individual | Separate for each member | Households wanting no shared-risk exposure; elderly parents | Costs more for the same total cover |
| Family Floater | One shared pool for all members | Young families, cost efficiency | One large claim can exhaust cover for everyone else that year |
| Top-Up | Activates above a deductible, per single claim | Cheap extra cover above a base policy | Pays nothing if no single claim alone crosses the deductible |
| Super Top-Up | Activates above a deductible, on combined annual claims | Almost always a better version of a top-up | Still requires a base policy or floater underneath it |
| Directional guide only — always confirm exact terms, sub-limits, and deductibles in the specific policy wording before buying. | |||